

How to Prevent Silent Write-Offs and Ledger Mismatches in Non-ChiroTouch EHRs
Non-ChiroTouch EHRs like Jane App hide silent write-offs behind automated billing logic. Learn how ledger mismatches form and how to catch them.
Silent write-offs and ledger mismatches in non-specialized EHRs are prevented through structured reconciliation processes rather than reliance on built-in automation. A silent write-off occurs when a patient balance or unpaid claim portion is removed from an account without documented approval, often through a default system rule rather than a deliberate billing decision. A ledger mismatch occurs when the amount recorded in the EHR for a patient account does not match the sum of payments received and approved adjustments. Non-specialized EHRs, including general practice management platforms not built specifically for chiropractic billing, often present these figures as reconciled even when underlying discrepancies exist. Prevention requires three coordinated practices. First, every adjustment or write-off must be tied to a documented reason code and require secondary approval before it posts to the ledger. Second, payment postings inside the EHR must be reconciled against actual bank deposits on a fixed schedule, rather than assumed accurate because the software marked a claim as paid. Third, patient portion and insurance portion calculations must be verified against the payer's explanation of benefits line by line, since automated splits inside general EHRs frequently misallocate coinsurance, deductible, and non-covered amounts. These practices catch discrepancies at the point they are created instead of allowing them to accumulate across hundreds of patient accounts. Without this layered verification, a system's internal reports can show a balanced ledger while the practice has still failed to collect amounts it billed and was owed, with no single report flagging the gap between the two figures.
What Counts as a Silent Write-Off (And What Doesn't)
Not every dollar that disappears from a ledger is a problem. A contractual adjustment is a legitimate, contract-bound reduction the practice agreed to when it credentialed with a payer. A silent write-off is neither agreed to nor documented — it just happens, buried in a default rule the software runs on its own.
The distinction matters because one is expected and the other is a leak. Confusing the two is exactly how a house-of-mirrors ledger stays standing. Every screen shows a balance, and the software never volunteers which entries were owed and which were simply erased.
| Adjustment Type | What Causes It | Is It Preventable |
|---|---|---|
| Contractual Adjustment | A fee schedule difference agreed to at credentialing, applied when the payer's allowed amount is lower than the billed charge. | Not applicable — this is an expected reduction, not a loss. |
| Denial Coded as Adjustment | A denied claim line gets absorbed into the adjustment field instead of being flagged for appeal or correction. | Preventable with a reason code requirement and secondary approval before posting. |
| Aged-Claim Auto Clear | A default system rule zeroes out a balance once a claim crosses an age threshold, regardless of whether it was ever paid. | Preventable by reconciling aged balances against bank deposits before any clearing rule runs. |
| Coinsurance Zeroed by Default | A patient's coinsurance balance is cleared automatically because the platform's default split logic misreads the explanation of benefits. | Preventable by verifying patient and insurance portions line by line against the payer's explanation of benefits. |
| Manual Override Drift | A rushed correction typed directly into the ledger during a busy afternoon, with no documented reason attached. | Preventable by requiring documentation for every manual entry before it affects the ledger. |
Contractual Adjustments Versus Preventable Write-Offs
A contractual adjustment exists because a fee schedule says it must. The payer's allowed amount comes in lower than the billed charge, the difference gets written off by agreement, and the account is genuinely settled.
A preventable write-off looks identical on the screen. But nothing authorized it. A denial got coded as adjusted, a coinsurance balance got zeroed by a default rule, or a claim aged past a threshold and the system quietly cleared it without anyone approving the loss.
How a Ledger Mismatch Actually Forms
A ledger mismatch occurs when the amount recorded in your EHR for a patient account does not match the sum of payments received and approved adjustments. That gap does not announce itself. It forms one small posting error at a time.
A misapplied payment, a partially processed remittance, a manual override typed in during a rushed afternoon — each one nudges the ledger away from reality. None of it shows up as an error. why clinical platforms weren't built for revenue cycle management explains how these small distortions compound inside general practice management platforms that were never built to catch them.
Why 'Automated' Ledger Logic Fails
Here's what most EHR dashboards are really selling: quiet confidence. Every screen looks balanced. Every batch reads closed, and nothing on the interface hints that a problem exists.
And that confidence is exactly the danger. The promise of billing that runs itself creates a blind spot, and that blind spot masks the process gaps where revenue actually leaks.
The Problem With Trusting Default EHR Reports
Most chiropractic practices on generic EHRs are losing money to silent write-offs, and they have no idea it's happening. The dashboard never stops to ask whether reconciled actually means correct.
That same blind spot shows up on the insurance side of the ledger. A breakdown of Why Jane App Insurance vs Patient Portion Math Leaves Revenue Uncollected walks through exactly where the split calculation goes wrong, long before a claim is ever submitted.
How Chiropractic Billing Loses Money by the Numbers
The house of mirrors comes with a price tag. Every silent write-off and every ledger mismatch traced so far lands somewhere in the aggregate numbers chiropractic practices report each year.
| Metric | Reported Figure | What It Measures |
|---|---|---|
| Average Annual Billings | $723,024 | The total amount billed per chiropractic practice across a full year, before any adjustments or collections are applied |
| Average Annual Collections | $450,425 | The actual amount collected per chiropractic practice after adjustments, denials, and write-offs are factored in |
| Billed-to-Collected Gap | $272,599 | The difference between what a practice billed and what it actually received, the space where silent write-offs accumulate |
| Medicare Chiropractic Claim Error Rate | 41 percent | The share of Medicare Fee-For-Service chiropractic claims flagged with errors, most tied to insufficient or incorrect documentation |
The Documentation Gap Behind Denied Medicare Claims
Denials do not always start with a payer decision. Many start with a documentation gap the EHR never flags before the claim leaves the office. As CMS reports, a 41 percent error rate on Medicare claims for chiropractic services in 2018 was most often caused by insufficient or incorrect documentation. Most of those errors traced back to insufficient or incorrect documentation, not to services that were not owed. A platform that promises the paperwork handles itself is the same platform that lets that gap go unnoticed until the denial lands.
The dollar figures make the pattern concrete. Work available through this published analysis indicates chiropractic practices bill an average of $723,024 annually but collect only $450,425, leaving a gap of approximately $272,599 per practice between what is billed and what is actually received — a finding from an industry survey. That gap did not come from one dramatic failure. It came from the same small, undocumented adjustments this section has been describing, repeated across a full year of claims.
Where Patient Portion and Insurance Portion Math Splits Apart
The mirror trick runs on this side of the ledger too. A screen can read balanced while patient math and insurer math were never once checked against each other.
Front-Desk Data Entry Points Where Splits Break
A miskeyed group number routes a claim down the wrong path before it is even submitted. That single entry error resurfaces later as a mismatch nobody traces back to the front desk.
Work available through the Provider Reimbursement Manual indicates Medicare bad debts must be derived from uncollectible deductible and coinsurance amounts owed by beneficiaries for Medicare-covered services, and providers must demonstrate that reasonable collection efforts were made before writing them off.
The same reasonable-effort standard shows up on the hospital side of Medicare bad debt too.
As HHS reports, Medicare requires hospitals to make a reasonable collection effort and establish that debts are uncollectible before claiming bad debts for reimbursement.
How Insurer Payment Timing Distorts the Ledger
Insurers do not pay on the practice's schedule. A remittance can land weeks after the EHR already posted an estimated patient balance.
A general EHR rarely tracks that timing gap, so the estimate sits on the ledger as if it were final. That is where chiropractic revenue cycle management built for chiropractic claims starts correcting the math before it hardens into a write-off.
Building a Reconciliation Architecture That Catches the Gap
Diagnosing the mirror is one thing. Building the frame that catches the gap before it hardens into a loss is another. A reconciliation architecture doesn't trust the dashboard — it checks that dashboard against outside evidence on a fixed schedule, every cycle, no exceptions.
Matching EHR-Posted Payments to Bank Deposits
Every payment the EHR marks as posted has to match an actual deposit in the bank. Not a batch total. Not an estimate.
The line-item comparison is what catches a misapplied payment before it becomes a mismatch nobody can trace back.
Auditing Adjustment Codes Before They Become Write-Offs
Adjustment codes are where silent write-offs hide best. Each one needs a documented reason and a second set of eyes before it posts.
These small, unapproved write-offs seem insignificant on a per-patient basis. Across a year of claims, they compound into thousands of dollars in lost revenue.
Sequencing a Weekly Ledger Review Without Adding Headcount
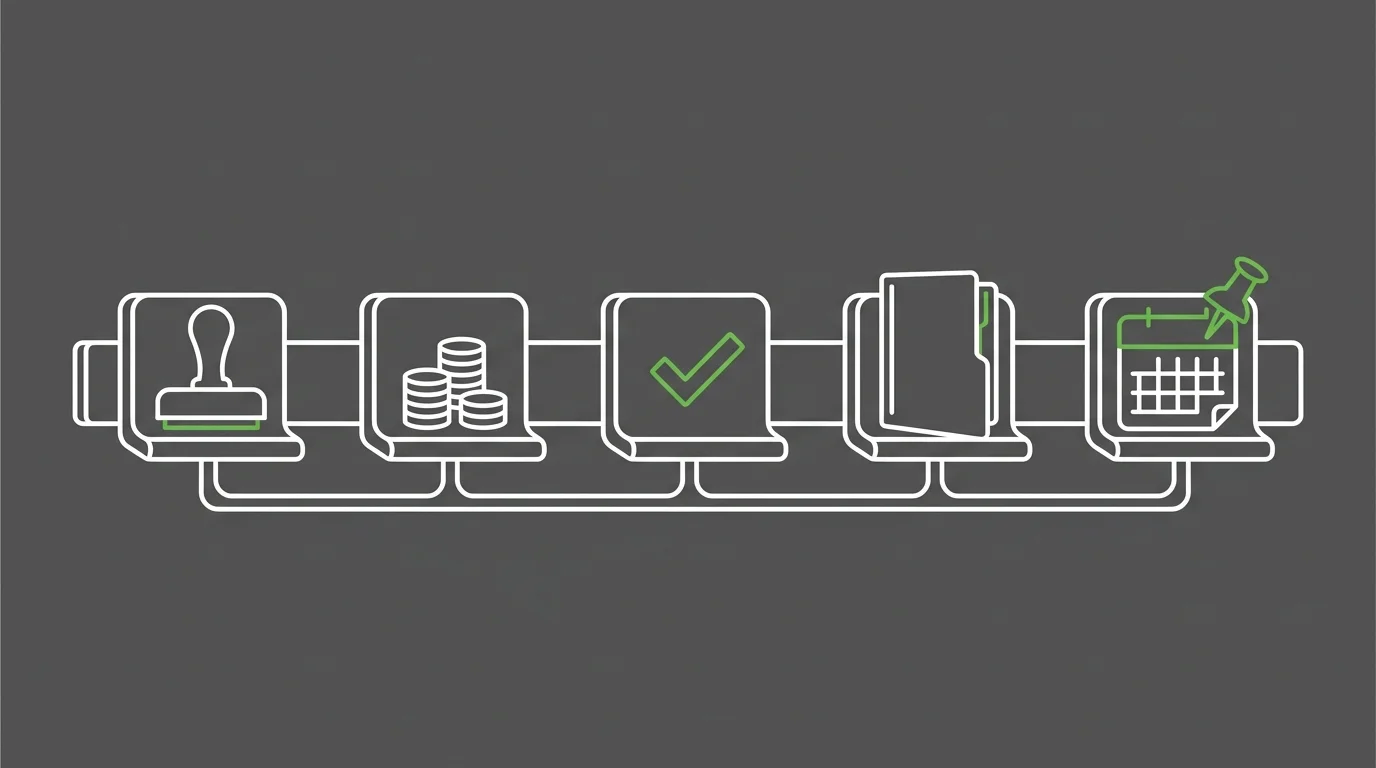
No practice needs a new hire to run this. It needs a sequence, repeated on the same day every week, so the mirrors get checked before the reflection drifts.
| Step | Task | Frequency |
|---|---|---|
| Step 1 | Match every payment the EHR marked as posted against the actual bank deposit, line by line. | Weekly, same day every cycle |
| Step 2 | Review every adjustment code entered that week and confirm each one carries a documented reason. | Weekly, same day every cycle |
| Step 3 | Verify patient and insurance portion splits against the explanation of benefits for that batch. | Weekly, same day every cycle |
| Step 4 | Scan aged claims approaching a write-off threshold before the system clears them automatically. | Weekly, same day every cycle |
| Step 5 | Confirm no balance moved without an approval trail, and assign one named owner per checkpoint. | Weekly, same day every cycle |
A Five-Step Weekly Reconciliation Sequence
Start by pulling every payment the EHR posted since the last review and matching it line by line against the bank deposit. Next, list every adjustment coded that week and confirm each one carries a documented reason. Then verify patient and insurance portions against the explanation of benefits for that batch. Follow with a scan of aged claims nearing a write-off threshold, and close by confirming no balance moved without an approval trail behind it.
Assigning Ownership for Each Ledger Checkpoint
Someone has to own each checkpoint by name, not by department. One person confirms deposits. Another approves adjustment codes. Split ownership across five steps is how a weekly sequence survives a busy week instead of quietly lapsing.
Frequently Asked Questions
The framework is clear once you have seen the mirror for what it is. A few specific questions still need direct answers.
What is a silent write-off and how is it different from a standard contractual adjustment?
A contractual adjustment is agreed to in the payer contract and written right there on the remittance. A silent write-off carries neither. It's buried inside a default rule the software runs on its own, with nobody's sign-off behind it.
How do simple data entry errors in an EHR lead to significant revenue loss over time?
A miskeyed group number or a wrong field routes a claim down the wrong path before submission. That single entry error resurfaces weeks later as an unexplained mismatch, and by then nobody traces it back to the original keystroke.
Why can't built-in EHR reports catch every patient ledger discrepancy?
Built-in reports confirm a batch got processed. They don't confirm the amount collected matches the amount owed. A dashboard will call a balance zeroed without ever checking it against a real bank deposit.
What are the top process mistakes that cause patient versus insurance portion mismatches?
The three recurring mistakes are treating insurance and patient portions as one calculation, posting an estimated patient balance before the remittance actually lands, and letting a secondary payer field go unchecked at intake. Each one distorts the split before a claim is even submitted.
How often should a chiropractic practice reconcile EHR payment postings against bank deposits?
Reconciliation belongs on a fixed weekly schedule, not a monthly or as-needed one. Waiting longer lets small posting errors compound before anyone notices the drift.
What documentation does Medicare require before a bad debt write-off is allowed?
Medicare requires proof that the debt is tied to covered deductible or coinsurance amounts and that a reasonable collection effort was made first. A write-off without that documentation trail does not meet the standard, for a practice or for a hospital claiming the same reimbursement.
Where This Leaves the Ledger
The mirrors were never going to fix themselves. A general EHR reflects whatever it was told to post — not what actually landed in the bank.
That gap closes only when a practice replaces default automation with a process-driven methodology built to check the reflection against reality. Reconciliation on a fixed schedule, documented adjustment reasons, verified splits — that is what a rigorous methodology looks like in practice, and nothing less catches a silent write-off before it hardens into a loss.
A practice that keeps trusting the dashboard will keep losing to the mirror. Bushido Billing built its process around checking behind the glass, and that conversation starts at book a call with Bushido Billing.