

How Far Ahead Should Clinics Start Commercial Re-Credentialing?
Chiropractic clinics should start commercial re-credentialing 90 to 150 days before expiration, since each payer runs its own cycle and documents take time.
Clinics should begin commercial re-credentialing 90 to 150 days before a provider's current credentialing cycle expires. The exact window depends on each payer's stated processing timeline. Commercial payers set their own re-credentialing cycles, and no single interval applies to all of them. Most payers require updated documentation well before the expiration date to prevent a disruption in claim payment eligibility. Re-credentialing verifies that a provider's license, malpractice insurance, National Provider Identifier record, and practice information remain accurate and in good standing. Initial credentialing establishes a provider with a payer for the first time. Re-credentialing confirms that the provider continues to meet that payer's existing standards. A lapse in re-credentialing status can cause a payer to treat the provider as out-of-network. Claims submitted during a lapse may be denied or reimbursed at a reduced rate until the credentialing file is reinstated. The lead time a clinic needs depends first on how many payers a provider is contracted with. It also depends on whether licenses or certificates must be renewed before submission. Payer processing speed is a third variable, since credentialing departments handle incoming applications at different rates. Clinics that maintain a current CAQH ProView profile typically avoid last-minute submission errors. Tracking each payer's individual re-credentialing date on a recurring schedule supports the same outcome. Commercial payer timelines are not standardized across the industry. For that reason, internal tracking systems are more reliable than a single universal deadline. Starting early creates a buffer for payer processing delays, document requests, and missing information. Without that buffer, these issues can stall approval and interrupt revenue.
What Re-Credentialing Actually Checks — And Why It Isn't Initial Credentialing Again
Re-credentialing is not a repeat of the first application. It is a status check, confirming a provider's existing file still holds up.
That distinction matters because clinics often treat the two processes as identical. They are not: one opens a relationship with a payer, the other verifies the relationship is still sound. Commercial re-credentialing is a recurring cycle, not a one-time event, and treating it as a single deadline is how clinics lose the rhythm.
The Difference Between First Enrollment And A Status Verification Cycle
Initial credentialing builds a provider's file from scratch. Licenses, insurance, NPI data and practice details all go in and get reviewed for the very first time.
Re-credentialing checks whether that same file is still accurate and in good standing. Nothing is being built. The payer is confirming that what it already has on record hasn't gone stale, which is exactly why clinics underestimate it — understanding what it takes to maintain commercial credentialing means treating the cycle as ongoing maintenance, not paperwork to file once and forget.
Why Treating Re-Credentialing As Paperwork Breaks Clinic Cash Flow
Plenty of clinics file re-credentialing under paperwork. That label gets wrong what the cycle is actually protecting: the clinic's ability to get paid.
A missed submission window does not just generate a late notice. It stalls claim payment eligibility, and the revenue gap shows up weeks after the cause has been forgotten. The real work of a schedule for re-credentialing an established clinic is less about hitting the payer's approval date and more about whether the clinic's own tracking system caught the deadline early.
Why Silence From A Billing Partner Is A Warning Sign, Not A Good One
A billing partner that stays quiet between deadlines is often read as low-maintenance. That reading has it backwards.
Proactive flagging of an upcoming re-credentialing date, a missing document, or a payer delay is evidence the system is working. Silence does not mean nothing is wrong. It means nothing has been caught yet, and a credentialing lapse surfaces as a cash flow crisis only once it is too late to prevent.
The Assumption That Breaks Practices: Billing Runs Itself Once It's Handed Off
The idea that credentialing runs itself once it is handed off treats a payer relationship like a filed document instead of a maintained account. It does not survive contact with how commercial payers actually operate.
A re-credentialing file only stays current if the information behind it stays current. That requires an EHR that a billing partner can actually see, provider availability for signature requests, and documentation that gets returned instead of sitting in an inbox.
Disengagement does not pause the clock. It just removes the people who would have caught the problem before the deadline did.
A practice that stops responding to requests between deadlines gets the same outcome as one that never built a system at all. The post-approval checklist for resuming billing exists because the work does not end at approval, and neither does the cooperation that keeps the next cycle on schedule.
What Medicare's Revalidation Rule Shows About Payment Delays
Medicare revalidation has its own deadline. CMS advises providers to submit their revalidation application to their MAC within 6 months of the due date to avoid a hold on Medicare payments and possible deactivation of Medicare billing privileges. That's the same quiet kind of lapse that turns into a cash flow crisis, and a clinic that ends up needing AR cleanup and revenue recovery after a missed deadline is paying for a problem steady tracking would've caught first.
How A Credentialing Lapse Spreads Through The Rest Of The Revenue Cycle
One expired credentialing status does not stay contained. It moves.
A denied claim from a lapsed status gets reworked, resubmitted, and often denied again before anyone traces it back to the credentialing file. By the time the pattern is visible, the backlog is already weeks deep.
The Chain Reaction From One Expired Status To A Denial Backlog
Here's the frustrating part: the EHR filed that claim correctly, and it still came back denied. The software that submits a claim has no way to tell a payer the provider's status lapsed.
That's where the idea that the EHR takes care of billing falls apart: software files the claim, but a lapsed status, the appeal and the AR recovery that follows all need a person who reads the denial and fixes the cause.
How Commercial Timelines Compare To Medicare's Revalidation Clock — And The Document Sequence That Keeps Either On Schedule
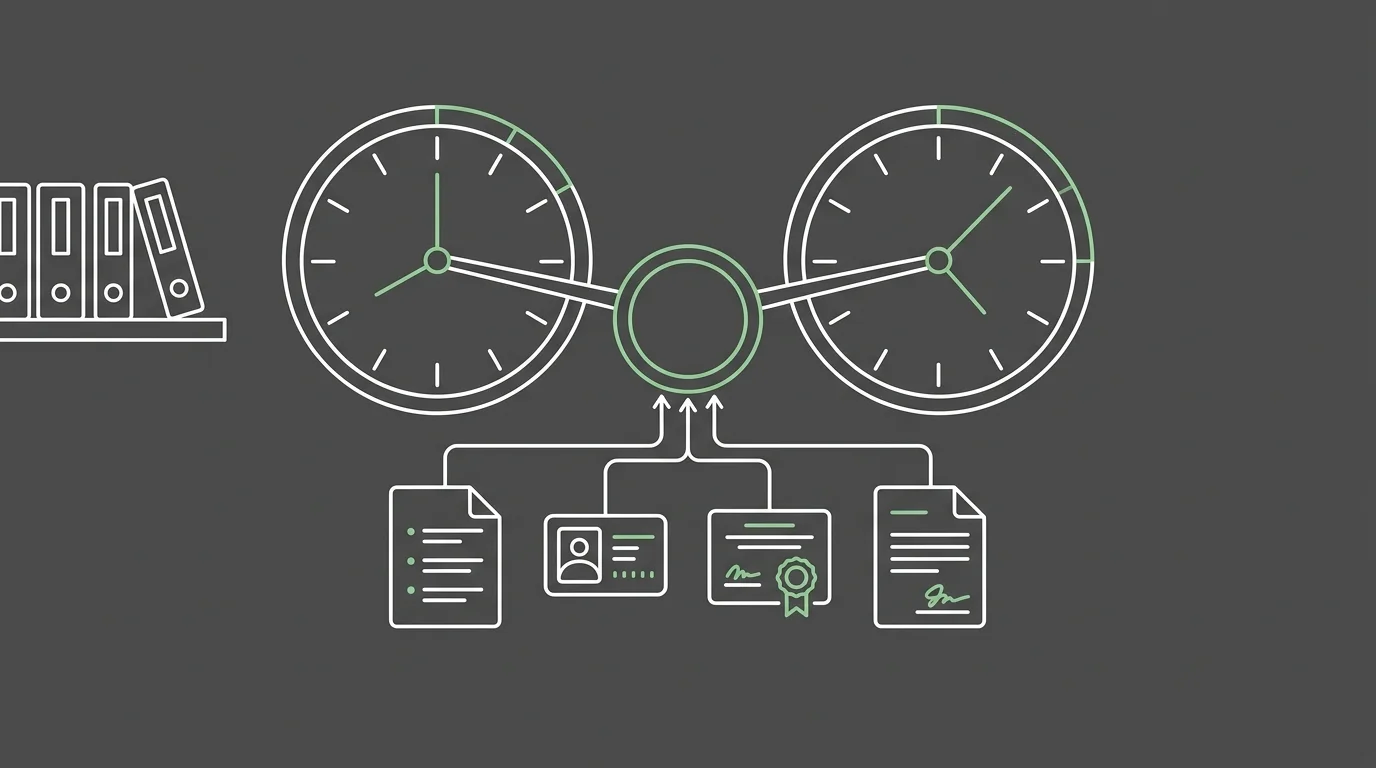
Medicare runs on a federal clock. Commercial payers run on their own.
42 CFR Part 424, subpart P, governs Medicare enrollment, and per the Code of Federal Regulations, § 424.515 sets the requirements for reporting changes and updates to, and the periodic revalidation of, Medicare enrollment information. That framework applies only to Medicare. Commercial re-credentialing intervals are set payer by payer, with no shared federal standard behind them.
| Jurisdiction Or Payer Type | Recredentialing Interval | Governing Reference |
|---|---|---|
| Medicare | Revalidation tied to federal cycle under 42 CFR Part 424, subpart P | 42 CFR Part 424, subpart P, § 424.515 governs reporting changes and periodic revalidation of Medicare enrollment information |
| Virginia MCHIP providers | At least every three years | Virginia MCHIP recredentialing regulation |
| Document Or Task | When It's Gathered | Why It's Sequenced There |
|---|---|---|
| License and malpractice insurance verification | Gathered first, ahead of any other submission step | Both carry fixed expiration dates a payer checks immediately, so stale copies stall the entire file before review even starts |
| NPI and practice information updates | Gathered second, once license and insurance data is current | Confirms the payer's existing record still matches the provider's active details before anything else gets attested |
| CAQH attestation renewal | Gathered last, closing the sequence | Outdated attestation data pulls from a shared profile multiple payers rely on, so it has to reflect everything updated before it |
| Payer-specific re-credentialing interval tracking | Gathered on a recurring schedule, not at a single point | State and payer rules diverge, so a tracking system has to hold each payer's own interval rather than one assumed date |
| Medicare revalidation documentation under 42 CFR Part 424, subpart P | Gathered on the federal timeline set by that framework, separate from commercial cycles | Medicare's clock runs independently of commercial payers, so its paperwork can't be batched into the same sequence as the rest |
State And Payer Variation In Recredentialing Intervals
A three-year cycle in one state may not hold in another.
Virginia offers one example. Virginia's administrative code says providers under its MCHIP regulation must be recredentialed at least every three years. Other states and payers set their own intervals, and they diverge enough that a single assumed interval puts a clinic's tracking system at risk.
The CAQH ProView Profile As The Shared Record Behind Every Cycle
CAQH ProView is the record many commercial payers pull from before a re-credentialing cycle starts. One updated profile feeds multiple payer files at once, instead of repeating the same submission for each one.
A stale CAQH attestation can stall every payer connected to it at once, not just one.
The Document Set And Order That Keeps A Cycle Clean
A clean cycle depends on sequence, not just paperwork.
License and malpractice insurance verification comes first, since both expire on fixed dates a payer checks immediately. NPI and practice information updates follow, confirming the file still matches what is on record. CAQH attestation renewal closes the sequence, since it has to reflect everything updated before it. Out of order, the same documents produce delay instead of approval.
Frequently Asked Questions
These questions come up often. Here are straight answers.
What happens if my clinic misses a commercial re-credentialing deadline?
A missed deadline can drop a provider out of network. Claims filed during that gap can be held or denied until the payer reinstates the file, so treat a missed date as urgent and call the payer right away.
Can a clinic still see patients and submit claims while re-credentialing is in process?
Yes, in most cases a clinic can keep seeing patients. The risk sits on the claims side, where payment can stall until the payer confirms the file is current.
How does the re-credentialing process for commercial payers differ from Medicare?
Medicare revalidation runs on CMS's cycle, and CMS advises submitting the revalidation application to the MAC within 6 months of the due date. Commercial payers set their own intervals.
What are the most common documents required for a smooth re-credentialing cycle?
Current license, malpractice coverage, NPI and practice information, and a current CAQH attestation.
If a clinic switches EHR systems, does it need to go through re-credentialing with all payers again?
A system switch doesn't reset credentialing status with existing payers. It does mean updating practice records so the new EHR reflects the same accurate information payers already have on file.
How does a lapse in credentialing for one provider affect the entire clinic's revenue cycle?
One provider's lapse doesn't stay contained to that provider. Denied claims pile into the shared AR queue, and the backlog slows cash flow for the entire clinic before anyone traces the cause.
Where This Leaves The Clinic's Revenue Cycle
The re-credentialing clock never stops ticking. It just gets ignored until a denied claim drags everyone's attention back to it.
Treat re-credentialing as one deadline, and the next one will catch a clinic flat-footed every time. Treat it as a maintained rhythm, and those deadlines stop being surprises. That rhythm runs on an EHR the billing partner can actually see, documents that come back instead of getting shelved, and a provider who's available when a signature is needed.
So here's the bottom line: the payer's calendar doesn't break the clock. Disengagement does, and keeping a practice's clock running starts with an honest look at where the gaps sit today, so book a call with Bushido Billing and start that conversation.