

What Is the Difference Between a DC-Led Billing Review and Generalist Data Entry?
DC-led billing review vs generalist data entry: how clinical peer review of chiropractic claims catches errors coding-only entry misses.
A DC-led billing review differs from generalist data entry in what each process is built to detect. Generalist data entry transcribes codes from a superbill onto a claim form, treating the task as clerical transfer of information from one document to another. A DC-led billing review treats the same claim as a clinical record to be evaluated, applying the judgment of a Doctor of Chiropractic to assess whether the codes, modifiers, and documentation actually support the treatment rendered. The distinction matters because chiropractic billing carries clinical nuance that transcription cannot interpret. Modifier selection, treatment classification, and documentation sufficiency all depend on understanding the clinical reasoning behind a visit, not just the numbers written on it. Generalist data entry accepts the superbill as given and moves it forward. A DC-led review reads the chart behind the claim, checking whether the coding matches the clinical picture before the claim ever reaches a payer. This peer-review function catches errors that occur at the intersection of clinical judgment and coding rules, a category of error that data entry is not structured to see because it never evaluates clinical content in the first place. The practical result is a claims process where accuracy is verified against the clinical record rather than assumed from it. Data entry asks whether the form was filled out correctly. A DC-led review asks whether the claim reflects what actually happened in the treatment room, and whether the documentation on file can defend that claim if challenged.
What Actually Separates a DC-Led Billing Review From Generalist Data Entry
Most practices treat billing as a clerical chore. The claim gets typed, submitted, and forgotten until a denial shows up.
Generalist data entry works this way by design. It transcribes codes from a superbill onto a claim form without evaluating the clinical reasoning behind them, which is exactly why errors born in the chart survive all the way to the payer. A DC-led billing review inverts that posture entirely. It functions as clinical peer review applied to the revenue cycle, reading the claim the way a chart is read rather than the way a form is typed.
Where the Line Gets Drawn
The line falls at judgment, not effort. A generalist can push a claim through fast and still miss what the codes don't justify.
That gap is structural, not a matter of carelessness. For a fuller account of how it plays out at scale, see an analysis of common generalist billing failure points.
Why Transcription-Only Entry Misses What It Isn't Built to Catch
Transcription-only entry fails quietly. The claim goes out clean, gets denied weeks later, and nobody can say why until someone reopens the chart.
That lag is what you pay for a workflow built to move paper, not read it. A data entry process copies what the superbill says. It was never built to ask whether the superbill was right.
What a Data Entry Workflow Is Actually Optimized to Do
Throughput is the whole point of a data entry workflow. Speed and volume are the metrics, and the codes on the page get treated as settled fact.
And nothing in that workflow stops to check whether a modifier matches the clinical picture it's supposed to describe. For a closer look at what that gap costs a practice's clinical bandwidth, see How Billing Failures Drain Chiropractic Clinical Focus.
How Modifier and Medical-Necessity Errors Compound Into Denials
Modifier errors are where the gap shows up. Medicare chiropractic manipulative treatment claims using HCPCS codes 98940, 98941, or 98942 must carry the AT modifier for services on or after October 1, 2004, or the claim gets treated as maintenance therapy and denied outright. According to CMS, must include the AT (acute treatment) modifier for services on or after October 1, 2004, or the claim will be denied as maintenance therapy. A transcriber can type that modifier correctly and still miss whether the visit actually qualifies as active or corrective treatment, because that judgment sits in the clinical reasoning, not the code.
The same rule holds regardless of how it is framed. Every Medicare chiropractic claim with a date of service on or after October 1, 2004, must carry the AT modifier when active or corrective treatment is performed, and its absence triggers denial as maintenance care. According to the CHIRO-001 billing and coding guidelines, the AT modifier on every chiropractic claim with a date of service on or after October 1, 2004, when active or corrective treatment is being performed, and claims without it will be denied as maintenance therapy. Data entry can satisfy that requirement on paper while missing it in substance, which is exactly the kind of failure a clinical read is built to catch.
How a Clinical Peer-Review Model Is Actually Structured
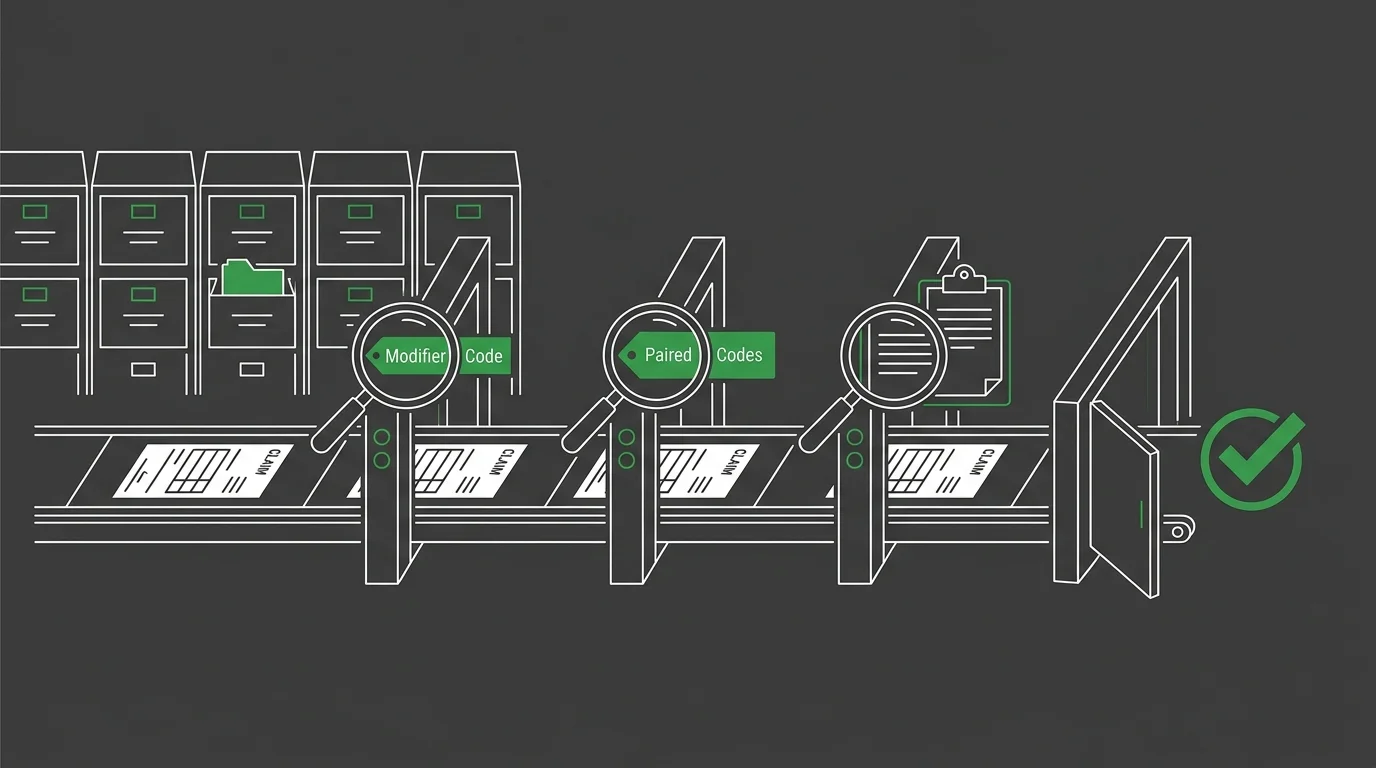
Peer review isn't one event. It runs at fixed checkpoints, not a single glance at the end.
A DC-led billing review works the same way. Each checkpoint reads the chart, not just the code sitting on top of it, catching the complex cases and payer-specific rules that generalist transcription has no mechanism to flag.
| Checkpoint | What Generalist Entry Does | What Clinical Peer Review Does |
|---|---|---|
| Pre-Submission Review | Transcribes codes from the superbill onto the claim form without checking whether documentation supports them | Checks documentation against the codes before the claim leaves the practice, confirming the clinical picture justifies what is billed |
| Modifier Selection | Applies the modifier that matches the code list, treating the choice as a formatting step | Evaluates whether the visit itself qualifies for the modifier, since that judgment sits in the clinical reasoning behind treatment |
| Denial Handling | Resubmits the claim as originally filed, sometimes correcting a field without asking why the denial happened | Diagnoses the denial against the chart, tracing the failure to its clinical or documentation source before refiling |
| Complex or Payer-Specific Cases | Applies a single standard workflow regardless of payer rules or case complexity | Adjusts the review to the specific payer requirement or clinical complexity, since generic transcription has no mechanism to flag either |
The Review Checkpoints Built Into the Claim Lifecycle
The first checkpoint lands before submission, where the documentation gets checked against the codes it's supposed to justify. It's also where a credentialing transition tends to surface gaps in how a practice's records were built. A practice weighing that shift can review How to Safely Transition EHR Credentials and Set Up a 30 Day Billing Timeline for what the move actually involves.
The second checkpoint lands after a denial, where the same clinical eye asks why the claim failed instead of firing it back unchanged. Data entry resubmits. A clinical read diagnoses.
What the Numbers Show About Chiropractic Claim Errors
The numbers back up what the checkpoint model predicts. Error rates in chiropractic billing aren't some edge case.
| Metric | Figure | What It Signals |
|---|---|---|
| Chiropractic claim error rate | 33.6% | Medicare's 2024 error review found errors this frequently among chiropractic claims examined, a scale that transcription-only review is not built to catch. |
| Review year | 2024 | The error rate reflects claims reviewed under the Comprehensive Error Rate Testing Program that year, not an isolated or outdated snapshot. |
| Documentation sufficiency | Common problem | Insufficient documentation was named as a recurring driver of these errors, the exact gap a clinical read is built to close. |
Reading the Medicare Error Data Against the Two Models
A Medicare error review examined chiropractic claims and put a documented error rate on the problem. Research published through the Medicare documentation checklist for chiropractors found insufficient documentation in chiropractic claims was identified as a common problem in a 2024 Medicare error review that found errors in 33.6% of claims examined. And insufficient documentation wasn't the rare exception here — it got named as a common one.
That figure describes claims processed under standard transcription review, not clinical peer review. Data entry checks whether a form was completed. It does not check whether the documentation behind it would survive scrutiny.
Why the Case-by-Case Argument Doesn't Hold Up
Some argue each denial is a one-off, fixed after the fact. That framing ignores where the error actually starts. A transcription-only workflow cannot see a documentation gap because it never reads the documentation. chiropractic revenue cycle management covers what a fuller claims process looks like once that reading happens at every stage. KFF found that in-network denial rates ranged from 3 percent to 36 percent depending on which insurer processed the claim in 2024.
Where the AT Modifier Rule Actually Gets Applied
The AT modifier rule is not an abstraction. It shows up on a specific line of a specific claim, tied to a specific code.
| Treatment Code | Modifier Required | Result If Applied Incorrectly |
|---|---|---|
| 98940 | AT modifier required for services on or after October 1, 2004 | Claim treated as maintenance therapy and denied |
| 98941 | AT modifier required for services on or after October 1, 2004 | Claim treated as maintenance therapy and denied |
| 98942 | AT modifier required when active or corrective treatment is performed | Claim without the modifier is denied as maintenance therapy |
Matching the Modifier to the Treatment Code
That is where transcription and clinical judgment part ways. Typing the modifier next to the code is mechanical. Deciding whether the visit earned it is not.
What Happens When the Modifier Is Missing or Misapplied
A missing or misapplied AT modifier does not get flagged by a workflow built to move paper. It gets flagged by a reader who checks the modifier against the chart before the claim ever leaves the building.
Frequently Asked Questions
A few mechanical questions come up once the distinction above lands. Here are the direct answers.
What specific types of errors does a DC-led review catch that automated software or a generalist might miss?
It catches the places where the codes and the clinical picture don't line up. Modifier selection, treatment classification, documentation sufficiency — none of those get evaluated by pure transcription, because none of them can be judged without reading the chart.
How does a clinical billing review impact the time it takes to get reimbursed by payers?
Catching errors before submission removes the delay a denial creates. A claim checked against the chart at the front end avoids the cycle of resubmission and appeal that follows a rejected claim.
What does the transition process from in-house data entry to a clinical review workflow actually involve?
Credentialing into a clinical review workflow starts with the chart and claim history already on file, not a blank slate. The review reads how documentation currently supports the codes being billed, then applies clinical judgment at each checkpoint going forward.
Can a clinical review process help with claims that have already been denied?
Yes. A denied claim gets reopened against the original chart to find why the documentation did not support the code, rather than resubmitted unchanged and hoping for a different outcome.
How does clinical documentation quality affect whether a claim gets approved?
Documentation is what a claim points to when it's challenged. Thin notes leave a correctly coded claim with nothing behind it, and nothing to defend the code when a payer asks.
What is the difference between active or corrective treatment and maintenance care for Medicare billing?
Active or corrective treatment addresses a condition expected to improve with care. Maintenance care preserves a current state without expected further improvement, and Medicare treats the two differently for reimbursement.
Why does a modifier error cause an entire claim to be denied instead of just flagged?
A modifier is not a side note on the claim; it defines what the code means. Get it wrong and the whole line reads as a different kind of care than what happened, which is why the entire claim fails rather than one field.
Where This Leaves the Claim Form
A claim form is a clinical document that happens to end in boxes and codes. It was never built to be typed blind.
Generalist data entry treats it as the second thing. A DC-led billing review treats it as the first, reading the chart before trusting the code sitting on top of it. That difference is the entire distinction this article has been describing.
A practice that keeps meeting denials with resubmission is treating a clinical failure as a clerical one. Reading the claim as a chart, before it leaves the building, is the only posture built to catch what transcription cannot see. That is the conversation worth having with Bushido Billing's team.