

How Do Payer Directory Errors and Missed Attestations Cause Chiropractic Claim Denials?
Learn how payer directory errors and missed CAQH attestations trigger chiropractic claim denials, and how a Revenue Gateway approach prevents them.
Payer directory errors and missed attestations cause chiropractic claim denials because insurers reject claims when a provider's on-file data does not match the information submitted at the point of billing. Every payer maintains a directory of provider names, addresses, tax identification numbers, National Provider Identifier data, and specialty codes. When a practice moves locations, adds a provider, or changes a group affiliation without updating that record, the payer's system flags the mismatch and denies the claim rather than resolving it manually. Attestation compounds this risk. Attestation is the formal process of confirming that a provider's data on file with a payer, or on a shared platform such as CAQH ProView, remains accurate. Payers require periodic re-attestation, and a missed deadline can cause a provider's record to lapse into an inactive or unverified status. Claims submitted while that status is inactive are denied on the basis of provider data rather than the clinical or coding content of the claim itself. This distinction matters because these denials are entirely preventable. They stem from administrative recordkeeping, not treatment appropriateness or documentation quality. A denial triggered by a stale address or an expired attestation requires the same appeal or resubmission effort as any other denial, consuming staff time and delaying payment for care that was properly rendered. The provider data a payer holds functions as a gateway that either releases payment or blocks it at the moment a claim is processed. Keeping that data current at every payer, on every platform, at every required interval determines whether a submitted claim moves toward payment or stalls at the first administrative checkpoint.
What Counts as a Payer Directory Error, and Why It Reaches Your Claims

A payer directory error is any gap between what a payer has on file and what a practice actually operates. Wrong address, wrong specialty code, wrong tax identification number. Any one of them breaks the match a claim needs to clear.
Attestation is the formal act of confirming that data is still correct. Payer directories rank among the top frustrations reported by both patients and providers, and a missed attestation is the mechanism that turns a passive directory listing into an active denial.
The Data Fields That Actually Trigger a Denial
Before a payer reviews anything clinical, it matches the claim against four fields: address, National Provider Identifier, tax identification number, and listed specialty. Miss on one, and the claim stops there.
Miss on any one of them and the match fails instantly, with no human weighing how bad the error is. You'll find the credentialing structure that keeps these fields aligned across every payer in an overview of how credentialing and CAQH enrollment shape revenue, and that structure is what stops the mismatch before it ever reaches a claim.
Directory Data Versus Attestation: Two Different Failure Points
Directory data and attestation are not the same thing. Directory data is the raw information on file. Attestation is the periodic confirmation that the information is still true.
A practice can carry accurate directory data and still get denied because attestation lapsed. The reverse also happens: attestation stays current while the underlying address is stale. Both failures block the same gateway, just from opposite directions.
The Reactive Fix-It-Later Method Doesn't Work
Here's how most billing operations run: a denial is the starting line. The claim gets rejected, staff pull the file, and the appeal begins.
That sequence feels like progress. It's actually the practice paying twice for one mistake — once in delayed revenue, and once in the staff hours spent fixing a problem that never had to exist.
Why Chasing Denials After Submission Fails the Practice
A claim denial is more than just a delayed payment. It is a drain on a practice's time and resources, and that drain repeats every time the same directory field goes stale.
By the time you're fixing a denial, the revenue was already blocked at the gateway. The appeal just reopens a door that correct data would have left open from the start.
What Gets Missed When Directory Review Only Happens After a Rejection
Review the directory only after a rejection, and you've already missed the window CMS-regulated payers actually work on. Work available through CMS indicates provider directory information must be available to current and prospective enrollees and the public within 30 calendar days of a payer receiving provider directory information or updates. That thirty-day window exists to keep records current — not to let a practice catch an error after a claim has already failed against it.
Medicare deficiency timelines leave even less room. As CMS's schedule of termination procedures reports, medicare terminates a provider's participation if compliance is not achieved within 90 calendar days following a survey. A provider found noncompliant loses participation outright once that ninety-day window closes without correction. Reactive review, by definition, only kicks in once the deadline is already at risk — and knowing the required cadence, covered in How Often Do Chiropractors Need to Re-Attest, is what keeps the gateway open on your schedule instead of closing on its own.
What the Denial Data Actually Shows
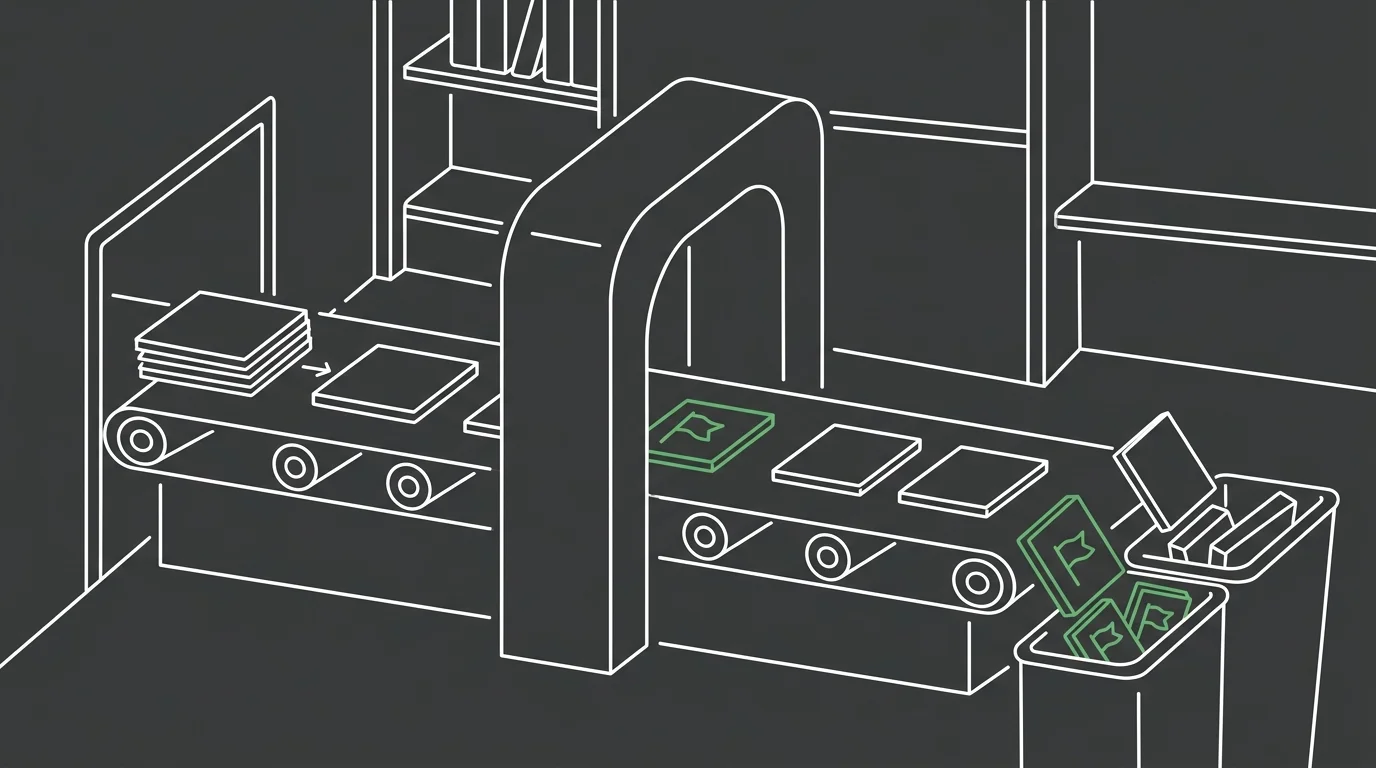
The scale of directory inaccuracy is not a minor footnote. It is the majority condition of the data payers actually hold.
As CMS's provider directory review report reports, 45.1% of provider directory locations in Medicare Advantage organizations were found to be inaccurate. That inaccuracy rate matches what happens when Medicare Advantage staff try to use their own directories. In one secret shopper study, staff attempting to schedule appointments with listed mental health providers succeeded only 18% of the time. A directory that fails at that rate is not a reference document. It is a liability sitting inside every claim submitted against it.
| Measured Finding | Figure | What It Covers |
|---|---|---|
| Directory inaccuracy rate | 45.1% | Provider directory locations reviewed across Medicare Advantage organizations found inaccurate |
| Denial rework cost | $25.20 | Average administrative cost to rework a single denied claim at a medical practice |
| Directory scheduling failure rate | 18% | Successful appointment scheduling attempts against listed Medicare Advantage mental health providers |
How a Reactive Denial-Chasing System Breaks Down Under Load
Chase denials one at a time and each rejection looks like an isolated event. It isn't. It's the predictable output of a directory system that was already broken before the claim ever left the office.
Work available through MGMA indicates the average cost to rework a claim is $25.20 — a finding from an industry survey. And that cost repeats across every stale field a practice never caught before submission. The rework spent fixing a wrong address is time not spent negotiating better terms — a subject covered in what commercial payers allow between fee schedule updates.
How Attestation Cycles Actually Work
An attestation cycle isn't one event you clear and forget. It's a checkpoint every payer runs on a schedule, and missing a single one closes the gateway until the next correction clears it.
| Attestation Component | What It Verifies | Typical Trigger |
|---|---|---|
| CAQH ProView Attestation | Confirms that provider demographic, licensure, and practice data on file match current reality | A re-attestation window opening or a data field changed since the last confirmed cycle |
| Payer-Specific Directory Update | Verifies that a single payer's own record of address, tax identification number, and specialty code is current | A location move, added provider, or group affiliation change reported to that payer |
| Medicare Enrollment Revalidation | Confirms continued eligibility to bill Medicare under existing enrollment data | A scheduled revalidation cycle or a deficiency notice requiring correction |
| Commercial Payer Roster Confirmation | Checks that a provider's listing in a payer's public directory matches what the practice actually operates | A periodic roster reconciliation request initiated by the payer |
CAQH ProView and the Standard Re-Attestation Window
Most commercial payers pull provider data from CAQH ProView rather than collecting it directly. A profile left unattested past its window reverts to an unverified state, and every claim tied to that provider inherits the same status.
And that reversion has nothing to do with whether the data is accurate. A provider's address and credentials can be perfectly current, and the claim still denies, because the attestation confirming that data was never renewed.
Payer-Specific Attestation Rules and Deadlines
Beyond CAQH, individual payers layer their own attestation rules on top, each with a separate deadline and a separate portal. A practice tracking only one calendar misses the others by design, not by accident. Coordinating that full picture, rather than reacting payer by payer, is the architecture behind chiropractic revenue cycle management.
Running a Directory Data Cycle That Doesn't Wait for a Denial
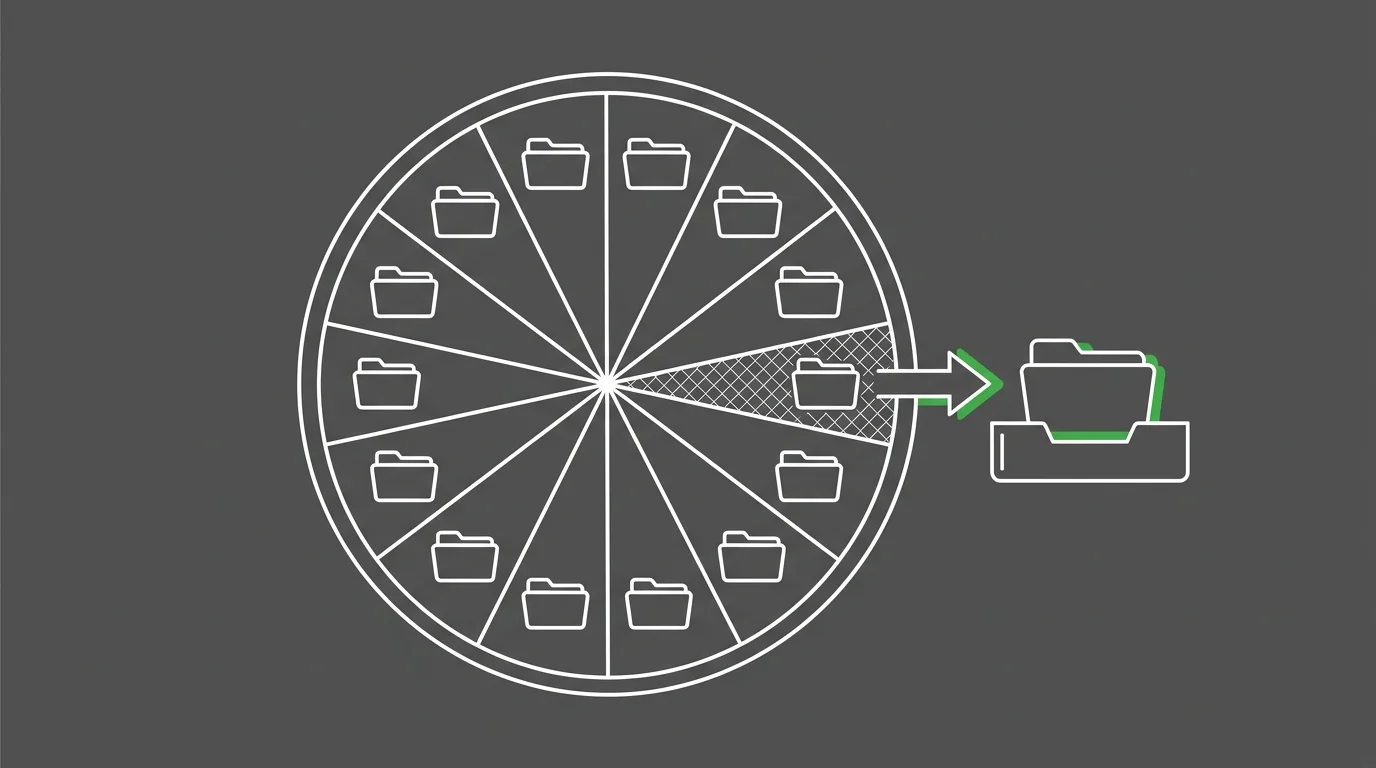
A gateway that opens once and stays open requires a cycle, not a calendar reminder. The work is checking every listing before a payer's system finds the mismatch on its own.
| Step | Action | Frequency |
|---|---|---|
| Pull Directory Listings | Compare every active payer listing against what the practice actually operates today, field by field | Fixed interval, run continuously rather than triggered by a denial |
| Log Attestation Deadlines | Record every payer's attestation window, including CAQH ProView, on one tracking sheet instead of separate logins | Ongoing, updated as each payer confirms or resets a deadline |
| Escalate Approaching Deadlines | Flag and correct any profile inside a set window before it reverts to an unverified status | Automatic, ahead of each payer's own cutoff |
| Verify Core Fields | Confirm address, National Provider Identifier, tax identification number, and specialty code match across every payer and platform | Reviewed on the same fixed interval as the directory pull |
| Document the Correction | Record what changed and when it was submitted to each payer, so a denial tied to old data can be resolved without rebuilding the history | At the time of every update, not after a claim fails |
Auditing Every Payer Directory Listing on a Fixed Schedule
Pull every active payer directory listing on a fixed interval and compare it line by line against what the practice actually operates today. A provider that loses participation entirely after a missed compliance window is the ceiling case. A quarterly review that catches a stale address before a claim hits it is the floor case, and it is the one that keeps revenue moving.
Logging and Escalating Attestation Deadlines by Payer
Every payer runs its own deadline on its own portal. Log each one on a single tracking sheet, never scattered across separate logins. Then escalate any deadline inside a set window automatically — before the profile reverts to unverified and every claim behind it stalls.
Frequently Asked Questions
The mechanics above raise specific questions every time they come up. Here are the direct answers.
What is a payer directory attestation and why is it required?
Attestation is the formal confirmation that provider data on file with a payer is still accurate. Payers require it on a schedule because unconfirmed data reverts to unverified status, and unverified status blocks claims regardless of how accurate the underlying information actually is.
Can a claim be denied simply because my office address is wrong in the payer's directory?
Yes. A payer's system matches claim data against its directory record automatically, with no human review of whether the mismatch is minor. A wrong address fails that match the same way a wrong tax identification number would.
What are the most common directory errors that lead to chiropractic claim denials?
Practice address, National Provider Identifier, tax identification number, and listed specialty code drive the most denials. These fields sit at the front of a payer's matching logic, so a change to any one of them without notifying every payer breaks the claims built on the old data.
What happens if a practice misses a payer's deadline for directory attestation?
The provider's record lapses into inactive or unverified status, and claims filed during that lapse deny on data grounds alone. Leave it uncorrected past a Medicare deficiency window and the lapse escalates to termination of participation.
What is a ghost network and how does it relate to directory accuracy?
A ghost network is a payer directory listing providers who are not actually reachable at the appointments or locations shown. The same inaccuracy that produces a ghost network for patients searching for care is what produces a denial for the practice behind that listing.
The Revenue Gateway Is Built Before the Claim, Not After the Denial
The gateway was never a figure of speech. Your directory data and attestation status are the switch that decides whether a filed claim moves toward payment or stalls at the very first checkpoint.
Fix that after a denial and you're just repairing a door that should have stayed open the whole time. Run it as a continuous cycle instead, checked against every payer before a claim goes out, and revenue keeps moving rather than piling up in appeals.
A practice that treats credentialing and attestation as recurring architecture, not a once-filed form, closes the gap where preventable denials live. That is the position worth building toward, and the place to start is a conversation about talk it through with us.