

How Often Can a Chiropractic Practice Renegotiate Commercial Insurance Fee Schedules?
How often can a chiropractic practice renegotiate insurance fee schedules? Learn the triggers, timing, and leverage points that actually reopen contracts.
A chiropractic practice can renegotiate a commercial insurance fee schedule whenever a specific contractual or operational trigger creates leverage, not merely once per year on a fixed anniversary date. Most payer contracts specify a defined renewal window, often requiring written notice within a set period before the contract term ends, and that window is the formal opportunity to reopen fee discussions. But calendar timing is only one trigger among several. Renegotiation opportunities also open when a practice adds a new credentialed provider, expands its service matrix with additional CPT codes, corrects an error in a payer's provider directory, or demonstrates updated outcomes and utilization data that were not available at the original contract signing. Each of these events changes the value a practice brings to a payer network, and that changed value is the basis for a renegotiation request regardless of where the practice sits in its contract cycle. Payer contracts frequently include automatic renewal language, sometimes called an evergreen clause, which extends the existing fee schedule unless a party takes affirmative action within a narrow notice period. A practice that tracks only the calendar date risks missing that notice period entirely. A practice that tracks its credentialing status, provider roster accuracy, and service offerings continuously is positioned to identify a renegotiation trigger the moment it appears, independent of the contract anniversary. The frequency of renegotiation is therefore governed less by a universal timetable and more by how actively a practice monitors the specific conditions that give it standing to ask for a different rate.
What a Fee Schedule Actually Locks In — And Why the Contract Date Isn't the Real Trigger
A fee schedule is the list of maximum fees a health plan will pay for specific services. It's the financial foundation of the whole provider-payer relationship. And most practices treat the anniversary date on that document as the one moment renegotiation becomes possible.
That assumption is backwards. The gateway opens and closes on credentialing accuracy, provider data, and service matrix changes — not the date printed on a contract. The full mechanics behind that shift live in how enrollment paperwork drives payment speed, because those are the details that actually reopen the gateway.
The Calendar-Only Approach to Renegotiation
Most in-house teams default to one move. They wait for the renewal date, then they ask.
That habit assumes the calendar is the trigger. It is not. Most payer contracts are designed to favor the insurer, containing language that makes proactive renegotiation challenging for providers, and a fixed annual glance at the contract does nothing to counter that design.
Why Waiting for the Annual Review Date Leaves Money on the Table
Waiting for the annual review date treats the gateway as a door that swings open once and shuts again. It doesn't work that way. The power dynamic in healthcare already leaves individual chiropractic practices feeling like they hold little leverage against large carriers, and an annual-only posture just deepens that feeling.
A missed provider directory correction or an unreported attestation can quietly stall a request long before the anniversary date even arrives. The mechanics behind that stall are covered in How Do Payer Directory Errors and Missed Attestations, and they explain why calendar-only tracking so often leaves the gateway shut.
How Contract Language Actually Governs Your Renegotiation Window
Waiting for the anniversary date is the flawed default. Most in-house teams default to a single move. They wait for the renewal date, then ask.
That habit assumes the calendar is the trigger. It is not. The contract itself decides when a window actually opens, and reading it as boilerplate is what leaves the gateway shut.
Notice Periods and Nonrenewal Windows
Notice periods define the real deadline, and Medicare managed care sets a hard example of how they work. As the U.S. Code reports, HMOs and CMPs must notify each Medicare enrollee by mail at least 60 days before the end of the contract period if they do not intend to renew.
Commercial payer contracts mirror that structure with their own notice windows, often shorter and less publicized. A practice that does not track its own contract's notice period on a rolling basis, alongside the credentialing and roster details covered in Chiropractic Credentialing and Enrollment Tracking, risks discovering the window only after it has already closed.
Termination-for-Cause Provisions
Termination-for-cause language works as the other half of this architecture. It defines the conditions under which a payer, or a practice, can exit the relationship entirely rather than simply renegotiate its terms.
Medicare's own framework sets the standard. As CMS reports, the Secretary may terminate a provider's Medicare agreement if the provider is not substantially complying with the agreement or applicable law and regulations. Commercial contracts carry comparable substantial-compliance clauses, and knowing them tells a practice whether it's negotiating from strength or standing on a gateway that could close under it.
The Events That Actually Reopen a Fee Schedule Conversation
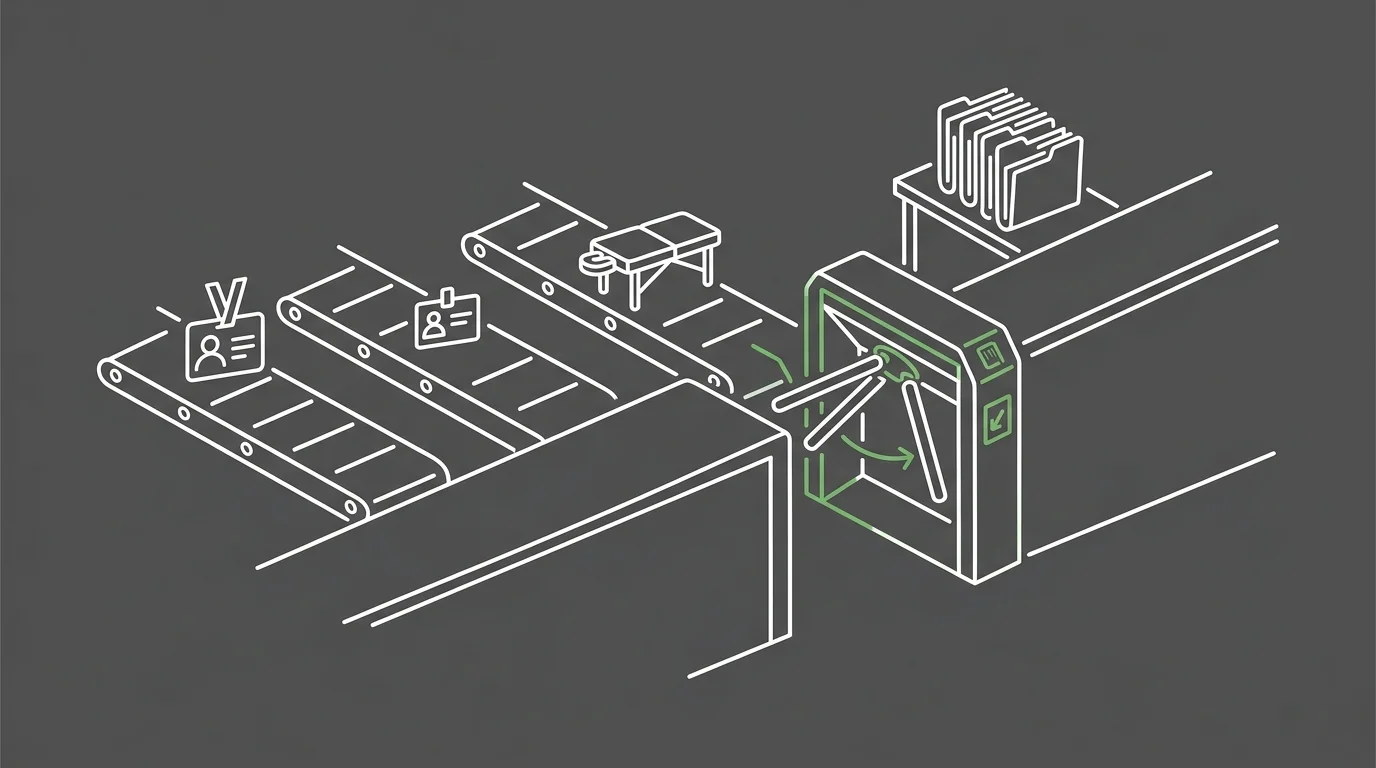
Static contract language draws the edges of the gateway. But what shoves it open mid-cycle is a real-world event — and those happen far more often than a renewal date ever does.
Credentialing Updates as a Renegotiation Trigger
Credentialing changes reopen the gateway because they change what a payer is actually contracting for. A new credentialed provider, a completed specialty designation, or a corrected enrollment record all shift a practice's standing mid-contract.
Annual Medicare rate changes show why this timing matters. On March 9, 2024, President Biden signed legislation that increased the Medicare Physician Fee Schedule Conversion Factor by 2.93 percent for the remainder of 2024, replacing an earlier 1.25 percent update. Findings published through the Physician Fee Schedule show the Medicare Physician Fee Schedule Conversion Factor was increased by 2.93 percent for the remainder of 2024 following legislation signed on March 9, 2024, replacing an earlier 1.25 percent update. A rate shift that large, arriving mid-year rather than on a contract anniversary, is exactly the kind of trigger commercial payers respond to as well.
Service Line Expansion and Provider Additions
Adding a service line works the same way. New CPT codes or an added associate provider expand the value a practice delivers, and that expansion is a valid reason to ask again.
The operational tracking behind these triggers is covered in chiropractic billing and revenue recovery, where credentialing and service data are managed as ongoing leverage rather than a once-a-year task.
Where Most In-House Billing Teams Lose the Leverage They Already Have
Plenty of practices already have a trigger sitting in front of them. A new provider gets credentialed. A service line expands. And still nothing happens, because possessing a trigger is not the same as converting it into a request.
The Data Gaps That Undermine a Renegotiation Case
The gap is usually data, not intent. Successfully renegotiating commercial insurance fee schedules is less about aggressive tactics and more about strategic preparation. Most in-house teams have the trigger event on file somewhere. Few have it packaged into the utilization numbers, roster accuracy, and service documentation a payer actually needs to see.
Building the Case Instead of Making the Request

A trigger only counts once it becomes a case. That means turning a credentialing update or a service expansion into a documented package a payer can actually sit down and evaluate.
| Trigger Type | What It Establishes | When It Applies |
|---|---|---|
| Credentialing Update | A change in provider status, such as a new specialty designation or a corrected enrollment record | Applies the moment the credentialing file changes, independent of the contract anniversary |
| Service Matrix Expansion | New CPT codes or an added associate provider that broaden what the practice delivers to the payer network | Applies as soon as the expanded service line is active and documented |
| Directory or Roster Correction | Accurate provider data that removes a payer's stated basis for holding a schedule in place | Applies once the correction is confirmed and reflected in payer records |
| Outcomes and Utilization Update | Updated performance data that was not available when the original contract was signed | Applies whenever current utilization numbers diverge meaningfully from the figures on file |
| Contractual Notice Window | The specific renewal or termination language that defines a valid window for a request | Applies on the schedule set by the contract itself, tracked continuously rather than checked once a year |
| Contract Mechanism | Governing Rule | Practice Implication |
|---|---|---|
| Automatic Renewal Language | Fee schedule carries forward unchanged unless a party acts within a defined notice window before the term ends | A practice must track its own notice period on a rolling basis or the current rate locks in for another term |
| Notice-of-Non-Renewal Requirement | Either party must give formal written notice ahead of the contract's end date to prevent automatic continuation | Missing this window forfeits the renegotiation opening entirely, regardless of how strong the underlying case is |
| Substantial-Compliance Clause | Defines the conditions under which either party can exit or terminate the agreement for cause | A practice out of compliance on credentialing or documentation negotiates from a weaker position than the data alone would suggest |
| Mid-Term Amendment Provision | Allows changes to specific contract terms, including rates, without waiting for the full renewal cycle | Credentialing updates or service expansions can be presented as grounds for amendment well before the anniversary date |
Benchmarking Against the Medicare Physician Fee Schedule
Medicare's annual conversion factor changes set a visible reference point for the whole industry. Commercial payers watch those shifts even though their own fee schedules move on separate timelines. A practice that references the current Medicare benchmark alongside its own claims data gives a payer a concrete reason to compare rates rather than default to the existing schedule.
Assembling the Documentation Package
The documentation package is where the trigger becomes real. Updated utilization numbers, corrected roster and credentialing records, and a clear account of any new service line all belong in it. A practice that assembles this before making contact is negotiating from a documented position.
Frequently Asked Questions
A handful of mechanical questions come up every time the gateway framing clicks. Here are the ones that matter most, answered straight.
What are 'evergreen clauses' in insurance contracts and how do they affect renegotiation?
An evergreen clause renews a fee schedule on its own unless someone gives notice inside a narrow window. Miss it, and the old rates ride for another full cycle.
What kind of data should a chiropractic practice prepare before requesting a fee schedule review?
Come with updated utilization numbers, a corrected provider roster, and current credentialing records. A documented service expansion makes the case even harder to wave off.
Can a small or solo chiropractic practice successfully renegotiate with a large national insurer?
Size matters far less than documentation. A solo practice with accurate credentialing data and a clean utilization record makes the same case a large group would.
Besides contract anniversary dates, what other events can trigger a fee schedule renegotiation?
A new credentialed provider, a corrected enrollment record, or an added service line all reopen the conversation. So does a completed specialty designation.
What is the first step to take if a commercial payer denies a request to renegotiate?
Read the contract's notice and termination language before you say anything back. A denial usually points to timing or missing documentation, not a closed door.
How do annual Medicare fee schedule updates impact what a practice can ask for from commercial payers?
Medicare's conversion factor shifts hand commercial payers a visible benchmark, even though their own schedules move on separate timelines. Pair that benchmark with internal claims data, and a payer has a concrete reason to compare rates.
What This Means for Renegotiation Timing
The calendar was never the gateway. What actually opens it is credentialing accuracy, provider data, and changes to the service matrix.
Manage those three continuously, and the gateway sits open far more often than it does for a practice that glances at it once a year. That isn't a tactic. It's the mechanism behind every fee schedule renegotiation that actually lands.
Bushido Billing builds its work around that mechanism rather than around a date on a renewal notice. If a practice wants to know where its own credentialing and service data actually stand, that conversation starts at Bushido Billing's services page.