

How Do Multi-Location Chiropractic Groups Manage Payer Panel Closures and Enrollment?
How multi-location chiropractic groups handle payer panel closures and structure provider enrollment so new locations reach revenue faster.
Multi-location chiropractic groups manage payer panel closures and enrollment by treating credentialing as a proactive revenue function rather than a reactive administrative task. This means monitoring panel status across every market before opening a new location, building delegated credentialing agreements with payers where eligible, and sequencing provider hiring around known network restrictions. When a payer panel closes to new providers in a given specialty or region, a practice cannot simply submit an application and wait for approval. Instead, groups pursue several parallel paths: requesting network adequacy exceptions, negotiating single-case agreements for individual patients, applying under a group National Provider Identifier when an existing in-network entity already holds a contract, and reassessing which locations can absorb new hires without triggering a fresh credentialing cycle. Delegated credentialing arrangements allow a qualifying organization to perform primary source verification internally under payer oversight, which shortens the enrollment timeline for new providers joining an already-credentialed group. Effective management also requires centralized tracking of every provider's status across every payer and every location, since a single missed re-credentialing date or expired license can silently close revenue at a site that was previously generating income. Groups that treat enrollment as a strategic gateway function build enrollment calendars, maintain payer relationship contacts, and evaluate new market entry against known panel restrictions before signing a lease or extending an offer. Groups that treat it as clerical paperwork discover panel closures only after a new provider is already on staff and unable to bill. The distinction between these two postures determines whether a location generates revenue on schedule or sits idle for months waiting on payer response.
What Counts as a Closed Payer Panel, and Why It Happens
A closed panel means exactly one thing. The payer won't process a new provider application for that specialty or region, no matter how clean the paperwork is.
Navigating the complexities of payer enrollment is a critical, yet often underestimated, challenge for growing multi-location chiropractic groups. Payer panel closures represent a significant barrier to revenue growth, effectively gatekeeping patient access and reimbursement for new locations or providers. A single-site practice can absorb one closure and wait it out. A group opening its fourth or fifth location cannot, because how enrollment status affects the revenue cycle compounds across every unfilled seat at every closed site.
Reading the Closure: Capacity Limits vs Network Adequacy Rules
Not every closure means the same thing, and treating them the same wastes real effort. A capacity closure says the payer already has enough providers in that specialty for the patient volume it sees in that region.
A network adequacy closure is a different animal. It's driven by a ratio the payer has to hold under state or federal rule, not by the payer's own call on how many providers it wants.
The Application-by-Application Trap: Why Case-by-Case Credentialing Breaks Down at Scale
One provider, one payer, one application. That method holds together right up until a second location opens with its own set of contracts.
Here's the flaw. The application-by-application method treats every new hire as an isolated event instead of one entry in a growing queue. It can't track thirty applications at once, because it was never built to.
| Enrollment Approach | Provider Groups Affected | Reported Daily Loss Range |
|---|---|---|
| Application-by-application credentialing | Health systems, hospitals, and provider groups | $1,000 to $5,000 per provider per day |
| Reactive enrollment (addressed only after a problem arises) | Health systems, hospitals, and provider groups | $1,000 to $5,000 per provider per day |
| Manual multi-clinic credentialing tracking | Health systems, hospitals, and provider groups | 69% report losses in the $1,000 to $5,000 per provider per day range |
Why Treating Each New Hire as a Standalone Enrollment Event Fails
The administrative burden of credentialing multiplies with each new clinic and provider, quickly overwhelming standard practice management workflows. A front office built to track one application at a time cannot scale to tracking dozens, each with its own payer, deadline, and document set.
A reactive approach to provider enrollment, where credentialing is only addressed when a problem arises, is a direct cause of revenue leakage and delayed patient care. State rules add another layer of failure, since a delegation agreement built for one state rarely transfers to the next. How Do State-Specific Credentialing Delegation Rules Affect Multi-State Chiropractic Groups breaks down why a single national process cannot substitute for state-level tracking.
What the Enrollment Delay Actually Costs a Provider Group
The cost of a stalled application is not abstract. A survey of healthcare leaders found that 69% of health systems, hospitals, and provider groups reported losses of $1,000 to $5,000 per provider per day due to payer enrollment delays. Research published through published trade reporting found 69% of health systems, hospitals, and provider groups reported losses of $1,000 to $5,000 per provider per day due to payer enrollment delays — a finding from an industry survey.
That figure covers health systems, hospitals, and provider groups, and the daily loss stacks up for every day an application sits unresolved. A group running the application-by-application method eats that cost again and again, once per hire, once per location, with nothing in place to shorten the wait.
Delegated Credentialing as a Structural Alternative to Panel-by-Panel Applications
Delegated credentialing removes the panel-by-panel bottleneck entirely. Instead of one application per provider per payer, a qualifying group performs primary source verification internally, under payer oversight, and enrolls new providers under the terms of a standing agreement.
The gateway stays open because the group controls the pace of verification instead of waiting on a payer's queue. That structural shift is what separates a group that scales credentialing from one that repeats the same bottleneck at every new location.
| Structural Element | Standard Panel-by-Panel Process | Delegated Credentialing Process |
|---|---|---|
| Application Path | Each provider submits a separate application to each payer, one at a time, per location | A single standing agreement covers new providers as they join the group |
| Verification Authority | The payer performs primary source verification and controls the timeline entirely | The qualifying group performs primary source verification internally, under payer oversight |
| Timeline Control | The group waits in the payer's processing queue with no ability to shorten it | The group sets its own verification pace within the terms of the agreement |
| Scalability Across Locations | Every new hire and every new site restarts the same per-payer process from zero | New providers enroll under the existing agreement without repeating the full application cycle |
| Governing Structure | No formal document beyond the individual application itself | A written agreement signed by both parties defines performance expectations before activity begins |
| Best Fit | A single provider entering a market where no standing payer relationship exists | A group with enough provider volume and administrative infrastructure to justify payer oversight |
What a Delegated Credentialing Agreement Actually Requires
Delegation is nothing casual. A practice has to execute a written document signed by both parties before any delegated credentialing work happens, and that document has to spell out performance expectations for both sides in specific terms.
Work available through published government guidance indicates a written document signed by both parties must be executed before delegated credentialing activities are performed, clearly defining performance expectations for both LHCC and the delegated entity. That requirement exists because the payer is trusting the group to perform work it would otherwise perform itself. Without a signed agreement defining those expectations, there is no delegation to speak of — only an informal understanding that a payer can revoke at will.
Where Delegation Fits and Where It Doesn't
Delegation fits a group with the provider volume and the administrative infrastructure to justify a payer's oversight investment. It doesn't fit a single new location walking into a market where no relationship exists yet.
Groups weighing whether delegation is worth building often want to see the return before committing the administrative lift it requires. What Is the ROI of Proactive Provider Credentialing breaks down what that investment returns against the panel-by-panel alternative.
Working a Closed Panel Without Delegation: The Appeal and Single-Case Route
Delegation is not always on the table. A newer location without the volume to justify a standing agreement still has to get providers enrolled somewhere.
That leaves the appeal route: challenging a closure directly, or negotiating a single-case agreement for one patient at a time while a broader solution takes shape.
Building the Case: Demonstrating Network Need to a Payer
An appeal only works if it answers the reason the panel closed in the first place. A capacity closure responds to evidence that patients in the area can't get seen within a reasonable timeframe. A network adequacy closure responds to almost nothing, because the ratio is set by rule, not by the payer's judgment.
Building that case means documenting wait times, referral patterns, and the gaps other in-network providers can't cover. It's patient-access evidence, not a paperwork resubmission. That same access problem that stalls a panel appeal tends to resurface later as a denied claim, which is where help with chiropractic claim denials becomes the next piece worth understanding.
Sequencing Enrollment When a Group Opens a New Location
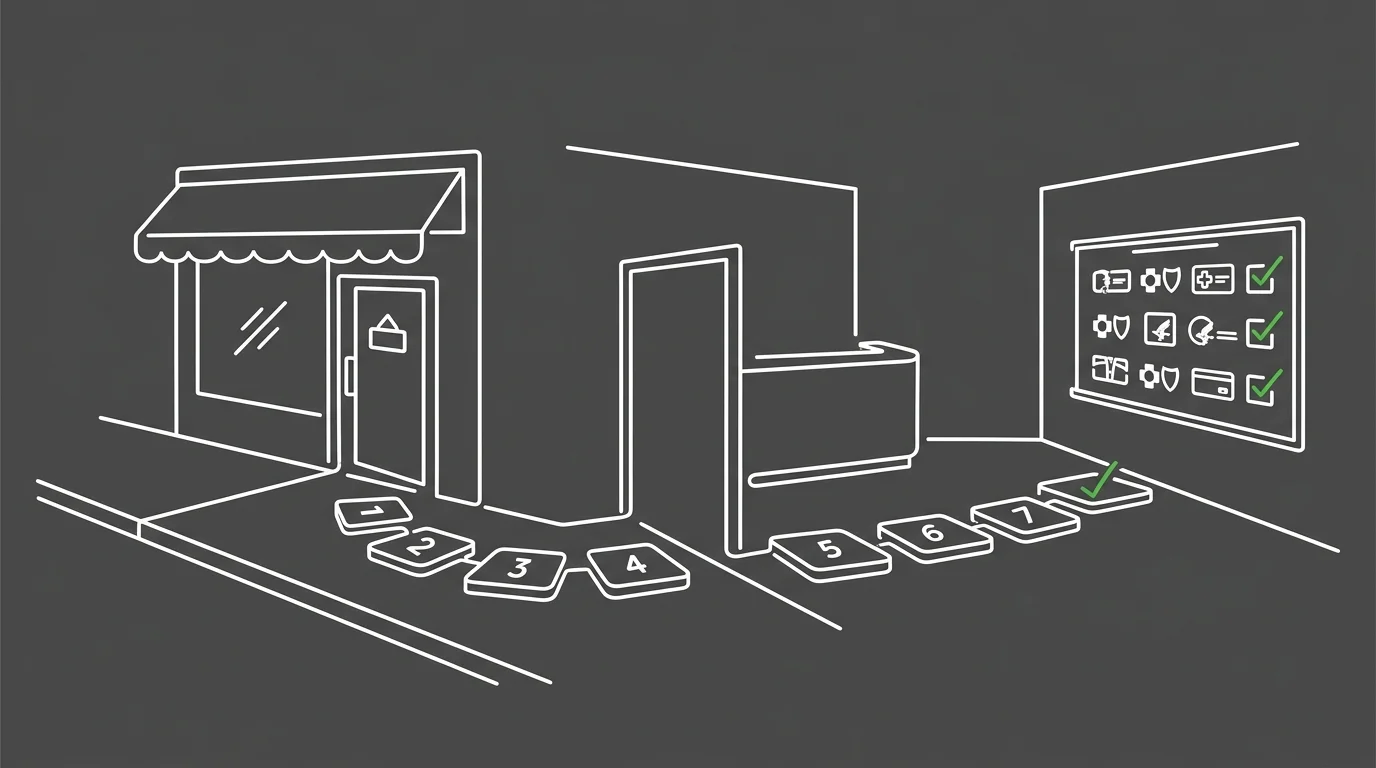
Opening a new location does not start with a lease. It starts with a sequence, and skipping steps is what leaves the gateway closed on move-in day.
| Sequencing Step | Trigger Point | Primary Risk if Skipped |
|---|---|---|
| Map payer panel status for the new market | Before a lease is signed or an offer extended | A location opens into a closed panel with no revenue path for the patients it sees |
| Confirm delegation eligibility against the group's provider volume | Once panel status is known for every payer in scope | A group defaults to panel-by-panel filing when a standing agreement could have shortened the timeline |
| Stagger provider hire dates against existing in-network contracts | When staffing a new site with a mix of new and already-credentialed providers | Every provider waits on a new payer contract instead of billing sooner under an existing group NPI |
| File appeals or single-case agreements where delegation does not apply | When a panel is closed and no standing delegation agreement covers that payer | The closure goes unchallenged even where a capacity argument could have opened an exception |
| Track every application, license, and re-credentialing date centrally | From the first filing through ongoing operation of the location | A missed date silently closes revenue at a site that was previously billing without issue |
Mapping the Payer Landscape Before the Lease Is Signed
Before signing anything, a group checks panel status for every payer it plans to bill in that market. Capacity closures, network adequacy limits, and delegation eligibility all vary by state and by payer, so this map has to be built site by site, not assumed from the last location that worked.
Staggering Applications Against Existing In-Network Status
Providers billing under an existing in-network group NPI can often see patients sooner than a provider stuck waiting on a brand-new payer contract. Stagger hire dates around that gap, and revenue keeps flowing at the new site while the slower applications grind through the queue behind it. Once the panel map and the staggering plan exist, the sequence is set: verify status, file where delegation applies, stagger hires against existing contracts, and track every date until the gateway is confirmed open.
Frequently Asked Questions
A few questions come up every time panel closures and delegation enter the conversation. Here are the direct answers.
What does it mean when a payer panel is closed?
A closed panel means the payer has stopped accepting new provider applications in that specialty or region. It does not mean the provider is unqualified, and it does not respond to better paperwork.
Are there exceptions or workarounds for a closed insurance panel?
Yes, but the workaround hinges on why the panel closed. A capacity closure can respond to evidence of patient access gaps, while a network adequacy closure set by regulation rarely budges.
How can a new chiropractor in a multi-location group get credentialed with a closed panel?
If the group already bills that payer under an existing in-network contract, the new provider can often see patients sooner while the payer processes a separate enrollment. If not, the group is filing a single-case agreement or an appeal while a longer-term fix takes shape.
What is delegated credentialing and how does it help multi-location practices with enrollment?
Delegated credentialing lets a qualifying group perform primary source verification internally, under payer oversight, instead of submitting one application per provider per payer. It requires a signed agreement defining performance expectations on both sides before any delegated activity happens, and it shortens the enrollment queue a growing group would otherwise repeat at every new hire.
What are the first steps when a key payer's panel is closed in a new service area?
Check panel status for every payer the group plans to bill in that market before a lease gets signed. Confirm whether delegation applies, whether existing in-network contracts cover the new site, then stagger hire dates around whichever route opens revenue fastest.
How does adding a new location impact existing provider credentialing with payers?
A new location does not automatically inherit an existing provider's in-network status with every payer. Each site typically needs its own enrollment confirmation, even when the group already holds a contract elsewhere, so credentialing has to be checked per location, not assumed from the last one.
What This Means
A closed panel isn't a dead end. It's a status that answers to one specific strategy — the one that fits the reason it closed in the first place.
Groups that map panel status before signing a lease, stagger hires against existing contracts, and pursue delegation where volume supports it keep the gateway open. Groups that wait for a payer's queue to move keep discovering closures after the offer letter is signed.
Credentialing decides whether a new location bills on schedule or sits idle waiting on a response. Treat it as the gateway it is, not the paperwork it resembles, and build the enrollment map before the next hire, not after. talk it through with us.